Inherited disease
Panels for cardiomyopathy, channelopathy, aortopathy, familial hypercholesterolaemia and pulmonary arterial hypertension.

Genomic and pharmacogenomic testing to clarify inherited cardiovascular disease, identify at-risk relatives and support selected treatment decisions.
Clinician-focused service: phenotype-led test selection, specimen coordination and family-testing guidance.
Panels for cardiomyopathy, channelopathy, aortopathy, familial hypercholesterolaemia and pulmonary arterial hypertension.
Support cascade testing and focused surveillance when a clinically relevant familial variant is identified.
Selected CYP2C19 and warfarin-response testing can complement clinical prescribing decisions.
Genetic testing is most informative when the phenotype, pedigree and clinical question are clearly defined. The panels below represent practical high-yield referral pathways.
Cardiomyopathy gene panel — unexplained HCM, DCM, ARVC, LV non-compaction or restrictive cardiomyopathy; early-onset heart failure; family history or sudden cardiac death.
Cardiomyopathy panel—expedited — the same indications when a faster result is clinically important.
Cardiac channelopathy gene panel — long-QT, Brugada, CPVT, short-QT, unexplained ventricular arrhythmia, cardiac arrest or sudden death.
Channelopathy panel—expedited — urgent inherited-arrhythmia evaluation.
Hypercholesterolaemia gene panel — severe LDL elevation, suspected familial hypercholesterolaemia, premature CAD or cascade screening.
Pulmonary arterial hypertension genetic test — idiopathic or heritable PAH, young-onset disease, family history or suspected PVOD/PCH.
Connective-tissue disorder / aortopathy panel — familial thoracic aortic aneurysm or dissection, syndromic aortopathy, or an overlapping Marfan–Loeys–Dietz–EDS phenotype.
Marfan syndrome—FBN1 analysis — aortic-root dilatation with Marfanoid features or family history.
Ehlers–Danlos syndrome gene panel — arterial fragility, aneurysm/dissection or syndromic connective-tissue findings.
Transthyretin—TTR sequencing — after ATTR cardiac amyloidosis is demonstrated, to distinguish hereditary ATTR from wild-type disease and guide family testing.
Fabry disease—GLA analysis — unexplained LV hypertrophy/HCM phenotype, especially with renal, neurological, dermatological or family findings. Consider GLA deletion/duplication analysis if sequencing is negative and suspicion remains.
Haemochromatosis gene panel — cardiomyopathy or arrhythmia accompanied by biochemical or radiological evidence of iron overload.
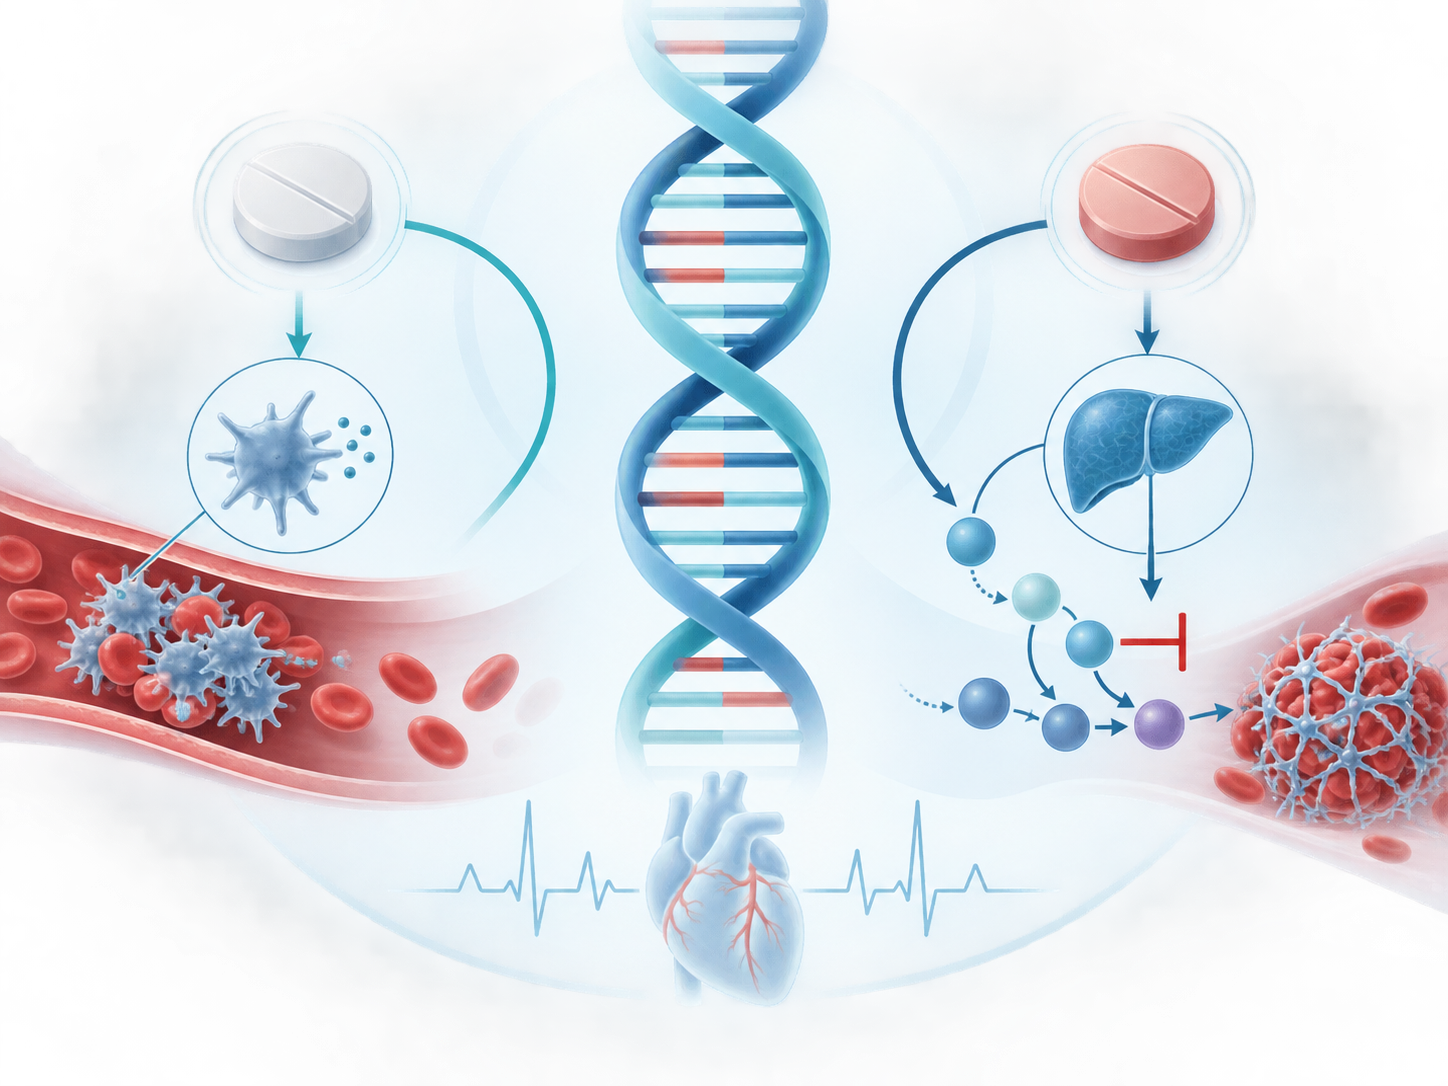
Use results alongside indication, comorbidity, concomitant treatment and current guideline recommendations.
CYP2C19 clopidogrel resistance—all CPIC alleles
Identifies loss-of-function and increased-function metaboliser phenotypes relevant to clopidogrel selection after PCI or ACS.
CYP2C19 *2 and *3 only
A faster, limited assay for the two major loss-of-function alleles; the broader all-CPIC assay is preferable when feasible.
Warfarin-response genotyping—VKORC1, CYP2C9 and CYP4F2
May support genotype-assisted initial dosing in selected patients; it does not replace INR monitoring.
Timing matters: Published turnaround is approximately 5–12 days for clopidogrel testing and approximately 12 days for warfarin genotyping. These tests are unlikely to guide an immediate emergency PCI decision unless performed prospectively.
These products are intended for risk stratification—not diagnosis—and should be interpreted with lipids, blood pressure, diabetes status, smoking, family history and validated clinical risk scoring.
Estimates inherited polygenic susceptibility to coronary artery disease.
Integrated CAD risk score combining genomic risk with relevant clinical factors.
Analysis-only pathway; contact the laboratory to confirm eligibility and required inputs.
CAD genetic-risk assessment together with a pharmacogenomic report.
Expanded combined genomic-risk and pharmacogenomic package.
Clinical note: These tests supplement—not replace—standard cardiovascular risk assessment. They are not diagnostic tests.
Testing should be selected according to the cardiac lesion, extracardiac features, developmental findings and family history.
Noonan syndrome gene panel — pulmonary stenosis, HCM or congenital heart disease with RASopathy features.
DiGeorge / 22q11.2 deletion–duplication by MLPA — conotruncal defects, interrupted aortic arch, hypocalcaemia or immunodeficiency.
FISH for DiGeorge/VCF syndrome — targeted 22q11.2 deletion testing.
FISH for Williams syndrome — supravalvular aortic stenosis with characteristic syndromic findings.
Alagille syndrome gene panel / JAG1 deletion–duplication — peripheral pulmonary stenosis with cholestasis or characteristic phenotype.
GDF1 and PKD1L1 sequencing (MGM1121) — selected heterotaxy/laterality-associated congenital heart defects.
Chromosomal microarray / KaryoTrack — multiple congenital anomalies, developmental delay or syndromic congenital heart disease.
All genomic tests are Out sourced to MedGenome Labs
Priority referral pathways: cardiomyopathy, channelopathy, familial hypercholesterolaemia, aortopathy/Marfan syndrome, pulmonary arterial hypertension, TTR amyloidosis, Fabry disease and CYP2C19 clopidogrel testing.
Specimen: Most assays accept peripheral blood in EDTA or direct DNA. Contact the laboratory before collection to confirm the current gene content, specimen requirement, price and turnaround time.